
Fluoxetine · How it works
How Does Fluoxetine Work?
Fluoxetine, commonly known by the brand name Prozac, is a selective serotonin reuptake inhibitor (SSRI) used to treat conditions including major depressive di
 Written by Sanjida Ahmed, PhD, Cellular and Molecular BiologyChief Operating Officer and Lead Scientist, Personalized Prescribing. Last reviewed October 2, 2026.
- Class
- SSRI (selective serotonin reuptake inhibitor)
On this page
- How Does Fluoxetine Work for Depression?
- What Does Fluoxetine Do to Serotonin?
- Why Does Fluoxetine Take Several Weeks to Work?
- What Is the Role of the 5-HT1A Receptor?
- What Is the Role of 5-HT2A and 5-HT2C Receptors?
- Why Can Fluoxetine Initially Increase Anxiety or Restlessness?
- How Does Fluoxetine Work for Anxiety?
- How Does Fluoxetine Work for OCD?
- How Does Fluoxetine Work for Bulimia Nervosa?
- Does Fluoxetine Affect Dopamine?
- Why Can Fluoxetine Cause Sexual Side Effects?
- How Is Fluoxetine Different from Citalopram or Escitalopram?
- Why Is Fluoxetine’s Long Half-Life Important?
- Why Do Fluoxetine Dose Changes Take Time?
- Why Does Fluoxetine Usually Cause Less Abrupt Withdrawal Than Some SSRIs?
- How Is Fluoxetine Metabolized?
- How Does CYP2D6 Affect Fluoxetine?
- Does CYP2D6 Genetic Testing Determine the Fluoxetine Dose?
- Fluoxetine Is Also a Strong CYP2D6 Inhibitor
- What Is CYP2D6 Phenoconversion?
- Can Fluoxetine Fail Even If You Metabolize It Normally?
- Can SLC6A4 Genetics Affect Fluoxetine Response?
- What About HTR2A Genetics?
- Can Pharmacogenomic Testing Tell Whether Fluoxetine Will Work?
- Why Can Fluoxetine Work Well for One Person but Not Another?
Fluoxetine, commonly known by the brand name Prozac, is a selective serotonin reuptake inhibitor (SSRI) used to treat conditions including major depressive disorder, obsessive-compulsive disorder (OCD) and bulimia nervosa. It is also used for several anxiety-related conditions depending on the country and clinical situation.
Fluoxetine works primarily by changing the way the brain uses:
Serotonin
Its main pharmacological target is the:
Serotonin Transporter — SERT
SERT normally removes serotonin from the space between nerve cells and transports it back into the serotonin-releasing neuron.
Fluoxetine blocks this transporter.
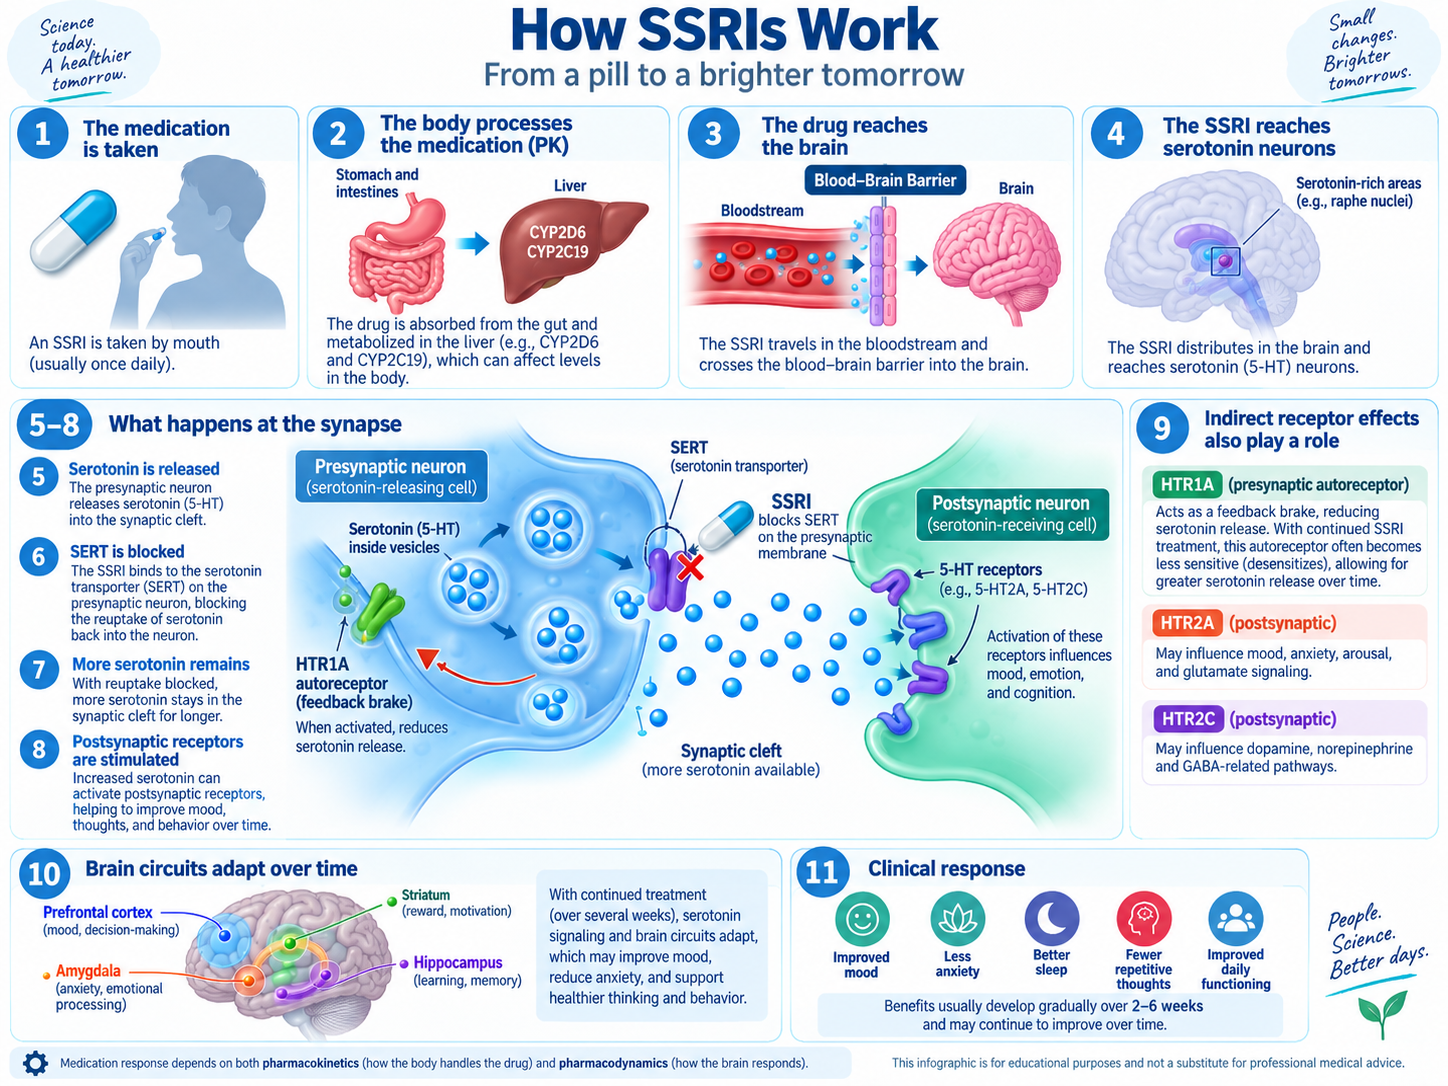
The basic pathway is:
- Fluoxetine
- Blocks SERT
- Serotonin reuptake decreases
- More serotonin remains available between nerve cells
- Serotonin receptor signaling changes
- Brain networks gradually adapt
- Depression, OCD or other symptoms may improve
The exact mechanism responsible for fluoxetine’s clinical benefits is not completely understood, but inhibition of neuronal serotonin uptake is considered its principal pharmacological action. Fluoxetine is much more selective for serotonin uptake than for norepinephrine uptake.
How Does Fluoxetine Work for Depression?
Depression is not accurately described as simply having “low serotonin.”
Major depressive disorder can involve dysregulation across several interacting brain systems responsible for:
- Mood
- Emotional regulation
- Stress response
- Motivation
- Sleep
- Concentration
- Reward and pleasure
- Negative or repetitive thinking Serotonin helps regulate many of these systems.
Normally:
- Serotonin is released
- Serotonin communicates with receptors on nearby neurons
- SERT transports serotonin back into the original nerve cell
Fluoxetine interferes with this recycling process:
- Fluoxetine blocks SERT
- Serotonin remains available longer
- Serotonin receptor activity changes
- Feedback mechanisms and neural networks gradually adapt
- Depressive symptoms may improve
Therefore, the therapeutic effect is not simply caused by “more serotonin.”
It involves the brain’s adaptation to altered serotonin signaling over time.
What Does Fluoxetine Do to Serotonin?
The serotonin transporter is encoded by the:
SLC6A4 gene
SERT functions like a recycling pump.
After serotonin has delivered a signal:
- Serotonin
- SERT
- Returned to the nerve cell
Fluoxetine binds to SERT and inhibits this process.
Therefore:
- Fluoxetine
- SERT inhibition
- Less serotonin is immediately recycled
- More serotonin remains available for signaling
This increased serotonin can interact with many receptor types throughout the brain.
Important serotonin receptors include:
- 5-HT1A
- 5-HT2A
- 5-HT2C
- Many additional 5-HT receptors The clinical response depends partly on how these different receptors and their associated neural pathways respond.
Why Does Fluoxetine Take Several Weeks to Work?
Fluoxetine begins inhibiting SERT relatively soon after it is taken.
Yet patients generally do not experience the full antidepressant effect immediately.
This is because:
Blocking SERT is only the first step.
Initially:
- SERT is blocked
- Serotonin availability changes
- Serotonin feedback receptors respond
Over time:
- Receptors adapt
- Intracellular signaling changes
- Neural networks adapt
- Emotional and cognitive processing changes
- Clinical improvement may develop
This process can take several weeks.
The prescribing information also notes that fluoxetine and its active metabolite accumulate gradually, with steady-state levels developing over roughly 4–5 weeks.
What Is the Role of the 5-HT1A Receptor?
An important serotonin receptor involved in SSRI response is:
5-HT1A
encoded by:
HTR1A
Some 5-HT1A receptors are located on serotonin-producing neurons and function as autoreceptors.
These receptors act like a feedback system.
When serotonin signaling rises:
- 5-HT1A autoreceptors are activated
- Serotonin-neuron firing may initially be restrained
With continued SSRI treatment, these feedback systems can adapt.
A simplified model is:
- Fluoxetine blocks SERT
- Serotonin availability increases
- 5-HT1A feedback initially limits serotonin firing
- Feedback system gradually adapts
- Serotonin signaling becomes differently regulated
- Therapeutic effects may develop
This is one proposed explanation for why the biochemical effect of an SSRI occurs rapidly but symptom improvement takes longer.
What Is the Role of 5-HT2A and 5-HT2C Receptors?
Increasing serotonin availability affects more than one receptor.
5-HT2A
is involved in areas such as:
- Mood
- Anxiety
- Cognition
- Arousal
- Sleep
- Sexual function
- Dopamine regulation 5-HT2C
can influence:
- Anxiety
- Appetite
- Reward
- Dopamine signaling
- Norepinephrine signaling
- Sexual function Therefore:
More serotonin
does not automatically mean:
More therapeutic benefit
The eventual effect depends on the balance of signaling across different serotonin receptors and different brain regions.
This helps explain why the same SSRI can improve anxiety or mood while also causing side effects such as:
- Restlessness
- Sexual dysfunction
- Sleep disturbance
- Appetite changes in some patients.
Why Can Fluoxetine Initially Increase Anxiety or Restlessness?
Fluoxetine is often considered one of the more activating SSRIs.
Some people experience early:
- Nervousness
- Restlessness
- Insomnia
- Jitteriness
- Increased anxiety This can happen because serotonin signaling changes rapidly, while receptors and larger neural circuits have not yet fully adapted.
The simplified process is:
- Fluoxetine starts
- Serotonin signaling changes
- Multiple serotonin pathways are activated
- Temporary activation or restlessness may occur
- Neural systems gradually adapt
- Anxiety may subsequently improve
Fluoxetine labeling recognizes anxiety and insomnia among clinically important treatment-emergent effects.
How Does Fluoxetine Work for Anxiety?
Although its approved indications vary by country, fluoxetine is also used clinically for certain anxiety-related disorders.
Serotonin helps regulate communication between brain regions involved in:
Threat detection
including the amygdala
and:
Emotional and cognitive control
including the prefrontal cortex.
Through continued SERT inhibition:
- Serotonin availability changes
- Serotonin receptors adapt
- Threat and emotional-regulation networks change
- Fear, anxiety and excessive emotional reactivity may decrease
This does not mean anxiety is simply caused by “low serotonin.”
Rather, fluoxetine may help improve dysregulated serotonin signaling within anxiety-related neural networks.
How Does Fluoxetine Work for OCD?
Fluoxetine is also used to treat obsessive-compulsive disorder.
OCD involves abnormal persistence of:
Obsessions
unwanted repetitive thoughts, images or urges
and/or:
Compulsions
repetitive behaviours or mental acts.
Brain networks involved in OCD include circuits connecting areas of the:
- Prefrontal cortex
- Striatum
- Thalamus
- Other cortical regions Serotonin contributes to regulation of these circuits.
A simplified model is:
- Fluoxetine
- SERT inhibition
- Serotonin signaling changes
- Cortical-striatal networks gradually adapt
- Repetitive thoughts and compulsive behaviours may decrease
The exact anti-obsessional mechanism is not completely established, and OCD often requires longer treatment before full benefit becomes apparent than some depressive symptoms.
How Does Fluoxetine Work for Bulimia Nervosa?
Fluoxetine is also used to treat bulimia nervosa.
Serotonin participates in neural systems involved in:
-
Appetite
-
Satiety
-
Impulse control
-
Reward
-
Compulsive behaviour
-
Emotional regulation By altering serotonin signaling, fluoxetine can reduce the frequency of:
-
Binge-eating episodes
-
Purging behaviours in some patients.
The exact mechanism is not fully established and should not be reduced simply to appetite suppression.
Its effect likely involves broader changes in serotonin-dependent impulse, reward and behavioural-control systems.
Does Fluoxetine Affect Dopamine?
Fluoxetine primarily acts on serotonin, not dopamine.
It does not directly block the dopamine transporter in the way that a medication such as methylphenidate does, nor does it release dopamine like amphetamine.
However, serotonin receptors interact with dopamine pathways.
Therefore:
- Fluoxetine
- Changes serotonin signaling
- Serotonin receptors influence dopamine neurons
- Dopamine signaling may change indirectly in certain regions
This serotonin-dopamine interaction may contribute to effects involving:
- Motivation
- Emotional processing
- Reward
- Sexual function
- Activation But fluoxetine is correctly classified as an SSRI, not a dopamine medication. Current labeling confirms that it is much more potent at inhibiting serotonin uptake than norepinephrine uptake and has relatively weak direct binding to many other receptor systems.
Why Can Fluoxetine Cause Sexual Side Effects?
Serotonin interacts closely with pathways controlling:
- Dopamine
- Sexual motivation
- Arousal
- Orgasm
- Ejaculation Increasing serotonin signaling can suppress certain dopamine and spinal pathways involved in sexual function.
Therefore:
- Fluoxetine
- ↑ serotonergic signaling
- Changes in dopamine and sexual-response pathways
- Possible:
- Reduced libido
- Delayed orgasm
- Difficulty reaching orgasm
- Delayed ejaculation
- Erectile difficulties This is a pharmacodynamic effect—it reflects how the brain and nervous system respond to increased serotonin signaling rather than simply how much fluoxetine is present in the blood.
How Is Fluoxetine Different from Citalopram or Escitalopram?
Fluoxetine, citalopram and escitalopram are all SSRIs.
All primarily work through:
SERT inhibition
However, they differ considerably in their:
- Metabolism
- Half-life
- Drug interactions
- Approved indications
- Tendency toward activation
- Pharmacogenomic relationships For example:
Citalopram and escitalopram
have a clinically actionable relationship with:
CYP2C19
whereas:
Fluoxetine
is strongly associated with:
CYP2D6 metabolism and CYP2D6 inhibition
but currently has no CPIC genotype-based dosing recommendation.
Why Is Fluoxetine’s Long Half-Life Important?
Fluoxetine is unusual among SSRIs because it remains in the body for a very long time.
After chronic use, fluoxetine’s elimination half-life is approximately:
4–6 days
Its active metabolite:
Norfluoxetine
has an elimination half-life of approximately:
4–16 days.
This means:
- A dose is taken
- Fluoxetine remains active for days
- Norfluoxetine remains even longer
- Active drug can remain in the body for weeks
This has several consequences.
Why Do Fluoxetine Dose Changes Take Time?
Because fluoxetine and norfluoxetine accumulate and disappear slowly:
Increasing the dose today does not produce the final new drug exposure tomorrow.
Similarly:
Reducing the dose today does not immediately remove the medication from the body.
Current labeling specifically warns that dose changes are not fully reflected in plasma concentrations for several weeks.
This means clinicians often need to allow sufficient time before judging the final effect of a dose adjustment.
Why Does Fluoxetine Usually Cause Less Abrupt Withdrawal Than Some SSRIs?
With a shorter-acting antidepressant:
- Medication stops
- Drug concentration falls rapidly
- Serotonin signaling changes rapidly
- Discontinuation symptoms may occur
With fluoxetine:
- Medication stops
- Fluoxetine remains
- Norfluoxetine remains even longer
- Active drug concentration falls gradually
- The medication effectively produces a partial natural taper
Current prescribing information notes that fluoxetine and norfluoxetine concentrations decline gradually at treatment discontinuation, which may reduce the risk of discontinuation symptoms.
However, stopping treatment should still be discussed with the prescribing healthcare professional.
How Is Fluoxetine Metabolized?
Fluoxetine is converted in the liver into:
Norfluoxetine
Norfluoxetine is particularly important because it is pharmacologically active.
It also inhibits serotonin reuptake.
So, the full pharmacological exposure is not simply:
Fluoxetine
It is better thought of as:
Fluoxetine + active norfluoxetine
The prescribing information identifies norfluoxetine as the principal active metabolite, with serotonergic activity that can be similar to the parent drug depending on the stereoisomer.
This becomes particularly important when considering genetics.
Fluoxetine is extensively metabolized in the liver.
CYP2D6
is an important pathway.
CPIC also identifies:
CYP2C9
as contributing to formation of certain norfluoxetine stereoisomers.
A simplified pathway is:
- Fluoxetine
- CYP2D6 + other pathways
- Norfluoxetine
- Fluoxetine + norfluoxetine both contribute to serotonergic activity
- Further metabolism and elimination
This makes fluoxetine pharmacokinetics more complex than medications that are simply converted into inactive metabolites.
How Does CYP2D6 Affect Fluoxetine?
People inherit different versions of the:
CYP2D6 gene
and can have:
- Poor
- Intermediate
- Normal
- Ultrarapid CYP2D6 metabolic activity.
A CYP2D6 Poor Metabolizer may process some forms of fluoxetine more slowly.
Therefore:
- Reduced CYP2D6 activity
- Higher parent fluoxetine
but also:
Less formation of some norfluoxetine
The important complication is that:
Fluoxetine is active
and:
Norfluoxetine is also active
Studies show CYP2D6 phenotype can significantly alter the parent-to-metabolite ratio, but the combined total of fluoxetine plus norfluoxetine may not differ consistently enough to support genotype-based dose recommendations.
Does CYP2D6 Genetic Testing Determine the Fluoxetine Dose?
Currently: Possibly.
CPIC reviewed CYP2D6 and fluoxetine and concluded that:
No gene-based fluoxetine dosing recommendation can currently be made.
The relationship is classified as: CPIC Level C
because there is insufficient evidence that CYP2D6 genotype consistently predicts total active exposure, effectiveness or safety in a way that supports a specific dose adjustment.
This is very different from medications such as: Atomoxetine where CYP2D6 phenotype has a well-established genotype-based prescribing guideline.
Fluoxetine Is Also a Strong CYP2D6 Inhibitor
This is one of the most clinically important features of fluoxetine.
Fluoxetine does not merely use CYP2D6.
It also:
Inhibits CYP2D6
Therefore, when fluoxetine is added:
- Fluoxetine
- CYP2D6 enzyme activity decreases
- Other CYP2D6 medications may be metabolized more slowly
- Their concentrations can increase
The current prescribing information specifically states that fluoxetine may cause a person with genetically normal CYP2D6 function to behave functionally like a Poor Metabolizer for another CYP2D6 substrate.
What Is CYP2D6 Phenoconversion?
Imagine someone is genetically:
CYP2D6 Normal Metabolizer
They begin fluoxetine.
Fluoxetine inhibits their CYP2D6 enzyme.
Therefore:
- Normal CYP2D6 genetics
- Fluoxetine
- Actual CYP2D6 activity decreases
- Functional metabolism may resemble a slower metabolizer
This is called:
Phenoconversion
The patient’s genes have not changed.
Their functional metabolic phenotype has changed because of the medication.
This can be important for medications such as:
- Atomoxetine
- Aripiprazole
- Brexpiprazole
- Risperidone
- Some tricyclic antidepressants
- Certain cardiac medications The label warns that CYP2D6 interactions may remain relevant even after fluoxetine has been discontinued because of its long persistence in the body.
Can Fluoxetine Fail Even If You Metabolize It Normally?
Yes.
Normal drug metabolism does not guarantee treatment response.
There are two major parts to medication response.
Pharmacokinetics — How the Body Handles Fluoxetine
Pharmacokinetics, or PK, includes:
- Absorption
- CYP2D6 + other metabolic pathways
- Fluoxetine + active norfluoxetine
- Elimination
- Drug exposure
PK helps answer:
Does an appropriate amount of active medication reach the brain?
But that is only the first step.
Pharmacodynamics — How the Brain Responds to Fluoxetine
Pharmacodynamics, or PD, describes what happens after fluoxetine reaches its target.
The first major target is:
SERT — SLC6A4
Fluoxetine blocks SERT.
Then serotonin interacts with receptors such as:
5-HT1A — HTR1A
5-HT2A — HTR2A
5-HT2C — HTR2C
and many additional serotonin receptors.
Therefore:
- Fluoxetine reaches the brain
- SERT is inhibited
- Serotonin availability changes
- Serotonin receptors respond
- Feedback systems and brain networks adapt
- Symptoms may improve
This means:
Normal PK does not automatically mean optimal PD response.
Someone can metabolize fluoxetine normally and still experience limited benefit if the serotonin system does not respond optimally for that person’s symptoms.
Fluoxetine Needs Both Drug Exposure and Brain Response
The complete process can be simplified as:
- Fluoxetine is taken
- Body absorbs and metabolizes fluoxetine — PK
- CYP2D6 + other pathways
- Fluoxetine + active norfluoxetine
- An appropriate active exposure reaches the brain
- Fluoxetine inhibits SERT — PD
- ↑ serotonin availability
- 5-HT1A + 5-HT2A + 5-HT2C + other receptors respond
- Serotonin feedback and brain networks adapt
- Depression, OCD or other symptoms may improve
So there are two different questions:
PK asks:
Does an appropriate amount of active fluoxetine reach the brain?
PD asks:
Does the serotonin system respond appropriately once it gets there?
Both contribute to the eventual clinical outcome.
Can SLC6A4 Genetics Affect Fluoxetine Response?
Fluoxetine’s principal pharmacological target is encoded by:
SLC6A4
which produces:
SERT — the serotonin transporter
Variants in SLC6A4, particularly the 5-HTTLPR region, have been extensively studied in relation to:
- SSRI response
- Remission
- Side effects
- Serotonin-transporter expression The biological rationale is clear:
- SLC6A4 genetics
- SERT biology
- Fluoxetine's primary target
However, clinical evidence has been inconsistent.
CPIC concluded that available evidence for SLC6A4 is mixed and insufficient to support its routine use for antidepressant prescribing.
Therefore, SLC6A4 should not currently be used alone to predict:
“Fluoxetine will work”
or:
“Fluoxetine will fail.”
What About HTR2A Genetics?
HTR2A encodes the: 5-HT2A serotonin receptor
Once fluoxetine increases serotonin availability, downstream serotonin receptors such as 5-HT2A influence the ultimate neural response.
HTR2A variants have therefore been studied in relation to antidepressant:
- Effectiveness
- Remission
- Tolerability
- Side effects However, CPIC similarly concluded that existing HTR2A evidence is insufficient for routine genotype-guided antidepressant prescribing.
The gene is biologically relevant, but it is not presently an established stand-alone prescribing marker.
Can Pharmacogenomic Testing Tell Whether Fluoxetine Will Work?
Not with certainty.
Fluoxetine response can depend on:
- Drug exposure
- CYP2D6 activity
- Other metabolic pathways
- Drug interactions
- Fluoxetine’s inhibition of CYP2D6
- SERT function
- Serotonin receptor signaling
- Symptoms
- Diagnosis
- Dose
- Treatment duration
- Previous medication response
- Individual brain biology Pharmacogenomic information may help provide part of a broader biological picture, but current CPIC guidance does not provide a CYP2D6-based fluoxetine dose recommendation, and neither SLC6A4 nor HTR2A currently has enough evidence for routine genotype-based antidepressant prescribing.
Why Can Fluoxetine Work Well for One Person but Not Another?
Two people with the same diagnosis may have very different underlying symptom patterns.
One person with depression may predominantly experience:
Sadness + anxiety + repetitive negative thinking
while another may experience:
Low motivation + fatigue + loss of pleasure + concentration problems
Although both carry the same diagnosis, the neurotransmitter systems and neural networks contributing most strongly to their symptoms may differ.
Response can also differ because of:
- Drug concentration
- Other medications
- Serotonin transporter biology
- Serotonin receptor activity
- Baseline neurotransmitter signaling
- Genetic variation
- Previous medication exposure This helps explain why an SSRI such as fluoxetine can be very effective for one person but less effective for another.
This article is educational. It does not diagnose, and it does not replace advice from your prescriber or pharmacist. Never start, stop or change a medication based on a web page.